PNEUMOTHORAX · HYPOXIA
Lung ultrasound
When to use it
- Rule out a pneumothorax after supraclavicular, infraclavicular, paravertebral, intercostal or chest wall blocks, or central line insertion.
- Check for one-lung (endobronchial) intubation.
- Find the cause of low oxygen in theatre or recovery: collapse, fluid in the lungs, pleural effusion, pneumonia.
- Probe
- Linear (pleura) or curved (deeper lung)
- Position
- Supine for pneumothorax; sitting or lateral for effusions
- Depth
- 4–6 cm for the pleura
How to scan
- Probe along the chest wall across two ribs. Find the ribs and the bright pleural line between them.
- For pneumothorax, scan the highest parts of the chest (front of the chest, 2nd to 4th intercostal spaces, in a supine patient).
- Look for sliding (a shimmer along the pleural line), B-lines and the lung pulse. Use M-mode to confirm: 'seashore' with sliding, 'barcode' without.
- For effusion and collapse, scan the back and base of the chest, just above the diaphragm.
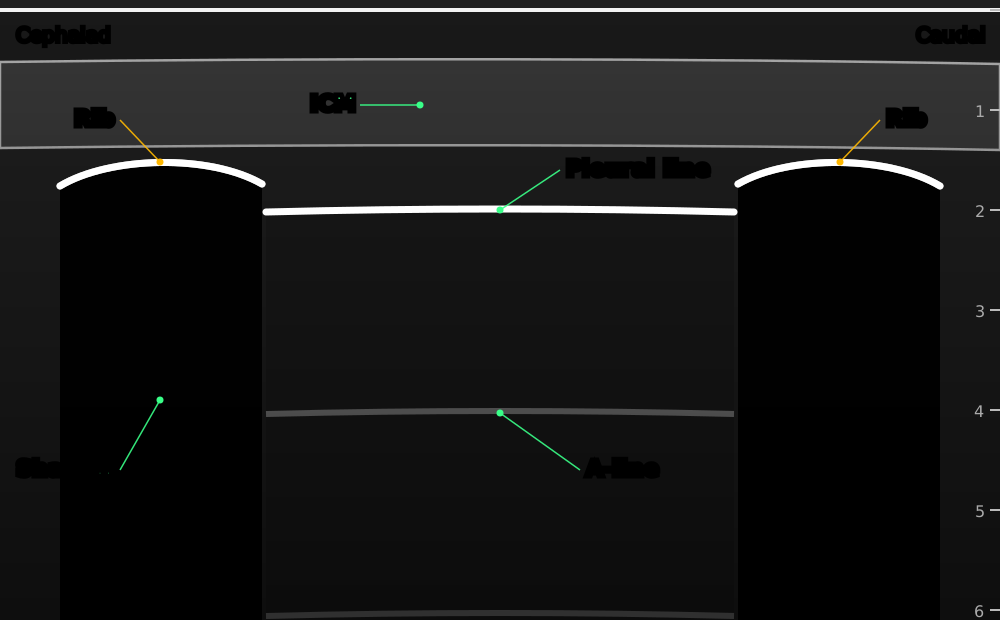
Probe along the chest wall across two ribs: the 'bat sign'. The pleural line lies between and just below the ribs.
- Rib
- ribs: the bat's wings, with an acoustic shadow under each
- Pleural line
- pleural line: shimmers back and forth when the lung slides
- A-line
- A-lines: horizontal repeats of the pleural line at equal steps, a normal air-filled lung
- ICM
- intercostal muscles
- Shadow
- rib shadow
Original schematic illustration © Nerve Blocks. Not to scale.
What you see and what it means
| On the screen | What it means |
|---|---|
| Sliding plus A-lines | Normal, air-filled lung under the probe: no pneumothorax there |
| No sliding, A-lines, no B-lines | Suspect pneumothorax; also seen with one-lung ventilation, apnoea, adhesions |
| Lung point: sliding meets no sliding | Pneumothorax confirmed (its edge) |
| Lung pulse but no sliding (left side) | Lung not ventilated: right main bronchus intubation |
| Three or more B-lines in one space | Interstitial fluid: pulmonary oedema, ARDS, pneumonia |
| Black space above the diaphragm | Pleural effusion |
| Tissue-like lung with bright air bronchograms | Consolidation or collapse |
Pearls
- Visible sliding or B-lines rule out a pneumothorax at that spot very reliably.
- No sliding alone is not proof: look for the lung point before acting, if the patient is stable.
- Compare both sides, and scan several spaces, not just one.
References
- Volpicelli G, Elbarbary M, Blaivas M, et al. International evidence-based recommendations for point-of-care lung ultrasound. Intensive Care Med 2012;38:577–91. PubMed
- Lichtenstein DA, Mezière GA. Relevance of lung ultrasound in the diagnosis of acute respiratory failure: the BLUE protocol. Chest 2008;134:117–25. PubMed
- Haskins SC, Tsui BC, Nejim JA, Wu CL, Boublik J. Lung ultrasound for the regional anesthesiologist and acute pain specialist. Reg Anesth Pain Med 2017;42:289–98. PubMed
